

End the Exploitation of Therapists: Demand Fair Pay & Structural LMFT Licensing Reform
The Issue
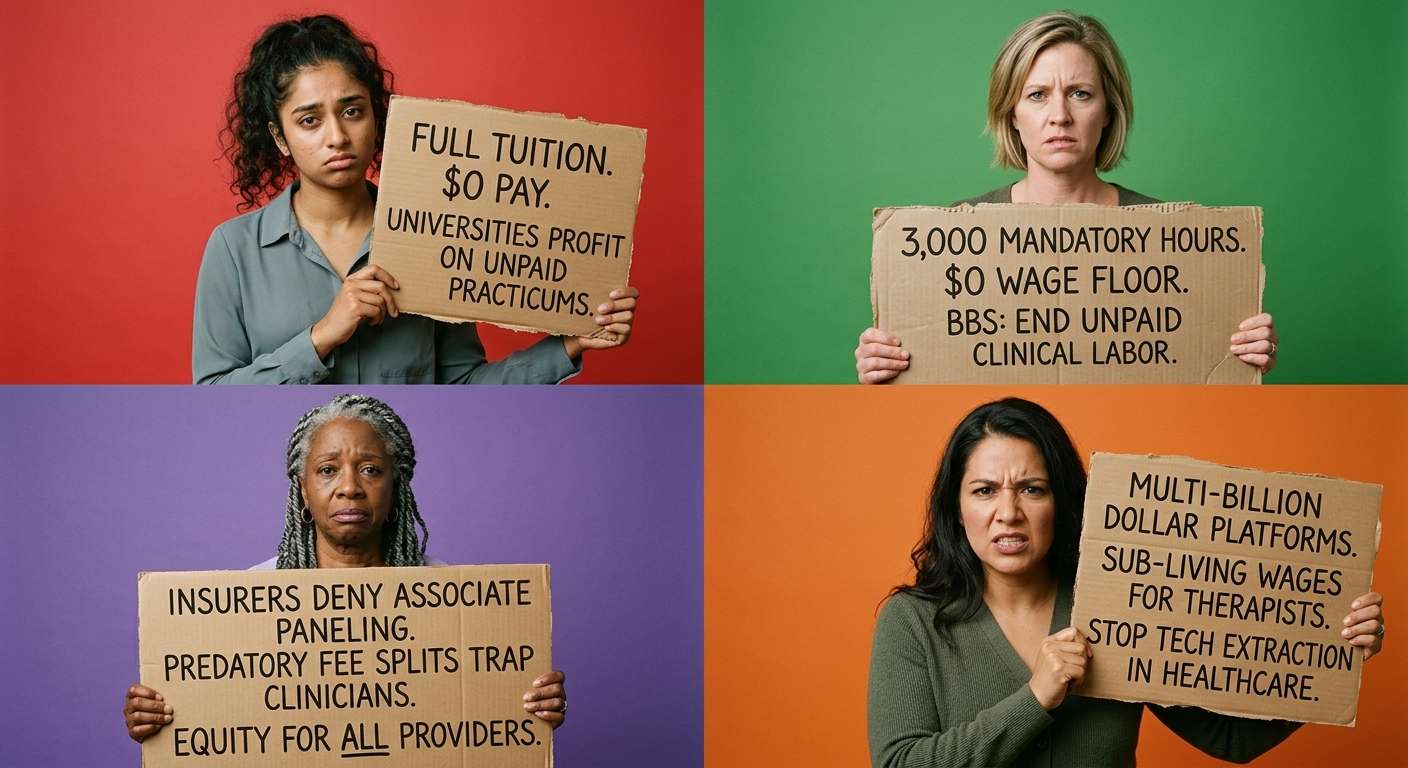
Systemic sexism is deeply embedded in the severely outdated structure of education and licensing for Licensed Marriage and Family Therapists (LMFTs).
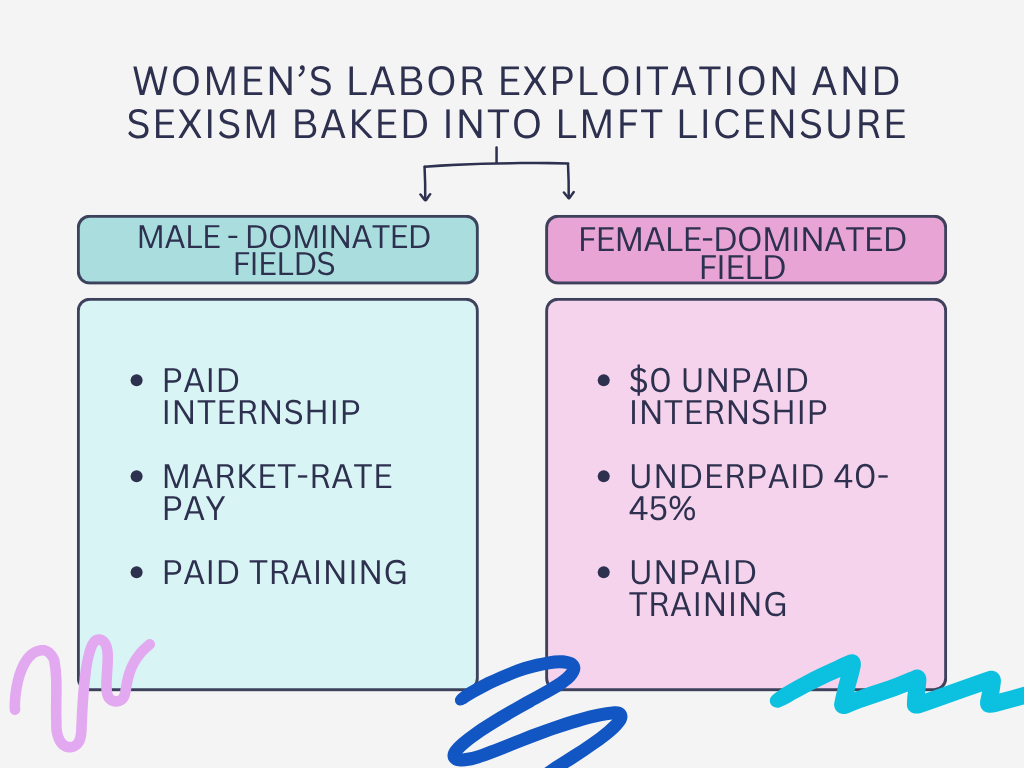
With 80% of the LMFT workforce being female in 2026, women continue to be systematically exploited through unfair, uncompensated practices masked as "training." It is wage theft.
While these systems claim to provide clinical experience, they unfairly enrich universities, licensing boards, commercial payers, and employers at the expense of therapists struggling to make ends meet under rigid, oppressive requirements.
These laws and regulatory structures are over 60 years old, anchored in mid-20th-century labor frameworks designed by male-dominated legislative bodies that viewed carework through an outdated, patriarchal lens. In 1963, the California State Senate had zero women. A legislature that was over 97% male drafted and voted on the foundational laws governing clinical training hours, supervision, and practice restrictions. This system strips women of economic freedom, trapping pre-licensed clinicians in engineered dependency. It is not just a professional hurdle it is a structural barrier to self-determination and financial independence.
California’s 3,000-hour mandate was modeled in the 1960s on an unrealistic 40-hour direct-care workweek. In modern practice, a sustainable 20-session client load generates 20 uncompensated hours of administrative and supervisory labor. What lawmakers framed as a two-year milestone is functionally a three- to five-year economic bottleneck one that traps and extracts years of unpaid labor from a predominantly female workforce and turns a master’s-level health license into an engine of gendered financial hardship.
The Bureaucratic Gauntlet: Engineered Exhaustion & Wage Theft
To earn a license in mental health, practitioners are subjected to an over-engineered, Kafkaesque administrative gauntlet that goes far beyond professional preparation it is designed to exhaust, gatekeep, and extract unpaid labor. The sad truth is that roughly 40% to 50% of people who graduate with an MFT degree ultimately achieve full licensure.
- The 3,000-Hour Trap: Pre-licensed clinicians are forced to navigate rigid, arbitrary sub-quotas mathematically balancing hundreds of mandatory hours across micro-categories like couples therapy, family systems, and specialized clinical settings all while wrestling with relentless weekly tracking targets and perfect 5:1 and 10:1 ratios for supervision.
- Pay-to-Play Compliance: Therapists must absorb thousands of dollars in out-of-pocket costs for mandatory continuing education (CE) units, specialized clinical certifications, supervision fees, and complex tracking software just to maintain their livelihood. In male-dominated technical fields, employers routinely absorb compliance and training overhead as a standard cost of business. In mental health, the financial and administrative burden is pushed entirely onto underpaid workers.
- The 36-hour Continuing Education (CE) requirement is an ongoing financial and administrative tax imposed every renewal cycle on mental health professionals. Therapists are forced to pay out-of-pocket for coursework and lose valuable clinical income just to maintain their licenses, whereas male-dominated technical fields routinely absorb these exact professional development costs as employer-provided overhead.
Real-World Proof of Pipeline Exploitation
- Sub-Minimum Wages for Master’s-Level Professionals: Associates earn just 40%–45% of the market rate. Cedars-Sinai—one of California's top health systems—pays pre-licensed clinicians a mere $21/hour on a mandatory 3-year contract with zero health benefits. Male dominated masters level careers offer 100% market rate.
- Hostile Barriers for Caregivers: Compulsory evening hours at health-tech agencies (e.g., Daybreak) conflict directly with peak caregiving times when parents need to be with their children. Restrictive site policies—like Airport Marina Counseling Center’s 3-hour interview process offered only a few times per year further exclude working parents.
- The Privilege Floor: Only a hardworking 10% of women in California hold a Master’s degree. Forcing clinicians through 3,000 post-graduate hours of unpaid or underpaid labor assumes they have external financial support, pricing out working-class women and single parents
The Four Drivers of Systemic Gender Exploitation
1. The Devaluation of "Carework" & The "Pink-Collar" Wage Penalty
Historically, patriarchal economics categorized emotional labor, active listening, and relationship maintenance not as specialized clinical skills, but as "natural" feminine traits. Because nurturing is treated as an intrinsic duty rather than an earned competency, female-dominated professions suffer a severe wage penalty: as an industry becomes majority-female, its compensation and prestige drop relative to male-dominated fields requiring equivalent degrees.
2. Paternalistic Gatekeeping & The Caregiver Ceiling
The massive 3,000-hour requirement is a 40 year old relic with exploitative 40% fee splits operates on the outdated assumption that female clinicians are secondary earners relying on a spouse’s income, have no healthcare needs or labor floor. There is no consideration on the idea that women want autonomy and economic freedom. Combined with a lack of subsidized childcare and flexible career pacing, women are expected to caretake at home, work, and for aging parents without support any institutional support. It does not consider the workforce of today.
3. The "Glass Escalator," The "Glass Ceiling," & The "Gilded Tier"
Structural authority remains concentrated at the top, regardless of workforce demographics. In male-dominated fields, women face the classic Glass Ceiling: while entering at equal rates, by age 40 only 30% make it into executive leadership.
In female-dominated fields like LMFT where 80% of therapists are women the system operates on the Glass Escalator: men who enter the field rise disproportionately faster to executive director positions, board chairs, and high-level administrative roles. Meanwhile, the apex of the commercial mental health industry for example keynote speakers, certification training gurus, and health-tech broker overlords remain heavily male-dominated, leaving the overwhelmingly female workforce governed by institutions that profit off their extracted labor. Also, these additional commercial modality trainings have no real over-sight, but many rules for therapists and can take an additional 2-3 years and $10,000-$20,000 in additional investment to compete in the field.
4. The Institutional Pyramid Scheme
- Venture-Backed Health Tech (Lyra, Grow, Headway, Alma): Capture $5B+ valuations by monetizing the gap between high corporate billing rates and capped therapist payouts while shifting non-clinical admin labor onto unpaid clinicians.
- State Licensing Boards (e.g., California BBS): Mandate 3,000 hours without establishing wage floors, overtime protections, or fee-split limits, trapping associates in a captive workforce. The 3,000-hour mandate holds master's-level therapists to a doctoral-scale post-graduate standard and bottleneck without providing any of the structural protections, W-2 benefits, or federal funding guaranteed in doctoral medical residencies. While prescribing providers like Nurse Practitioners enter independent practice immediately upon graduation, therapy associates are forced through a multi-year apprenticeship that disproportionately exploits relational carework for profit under the guise of an arbitrary, legacy training metric.
- Universities & Graduate Programs: Charge full tuition while relying on uncompensated student labor to build community partnerships instead of funding internal paid clinics. Also, requiring students to pay out of pocket for 16 sessions of their own therapy with a licensed therapist.
- Commercial Insurers (Kaiser, Anthem, Blue Shield): Refuse to panel associates directly, capturing employer premiums while fostering burnout environments.
7 Demands for Policy Reform
- Mandate Pre-Licensed Insurance Billing: Commercial insurers, Medi-Cal, and Medicare must reimburse pre-licensed clinicians under a supervisor’s NPI to unlock immediate living wages.
- State-Funded Mental Health Residencies: Public health budgets and general fund grants must directly subsidize Associate salaries and agency overhead as an essential public health investment.
- Pay for ALL Hours Worked: End piece-rate exploitation. Require employers to pay for every required work hour—including note-writing, client assessments, crisis management, and mandatory supervision.
- Establish Industry Fee-Split Standards: Cap private practice revenue extraction by establishing clear industry standards (e.g., 60/40 or 65/35 in favor of the Associate).
- Enforce Strict Mental Health Parity: Force insurance commissioners to equalize behavioral health reimbursement rates with medical/surgical specialties to raise financial standards across the field.
- Eliminate Board Bottlenecks: Fully fund licensing boards to eliminate months-long administrative delays that lock clinicians out of the active workforce while carrying massive debt. Board of Behavioral Sciences (BBS) to initiate an occupational and comparative analysis of the 3,000-hour mandate.
- Hold Universities & Sites Accountable: Re-evaluate barriers to entry, audit practicum sites for labor mistreatment, oppressive and unreasonable requirements, and dismantle systems built on uncompensated carework.
Gender-Equity Crisis and Systemic Labor Exploitation, new AMFT Registrations: Roughly 3,500 to 4,000 new Associate Marriage and Family Therapists (AMFTs) register with the BBS each year after graduating from their master's programs and receiving their degrees. Active Total Pool: At any given time, the state maintains a total active pool of roughly 15,000 to 18,000 active AMFTs working across California to complete their required hours. Forcing thousands of uncompensated hours on a predominantly female workforce during a mental health crisis is an equity failure that must be dismantled.
Stand With Us: End the Exploitation, Provide Fair Pay and Demand Structural LMFT Licensing Reform, advanced degrees require advanced compensation. California’s mental health providers deliver life-saving care it's time to replace institutional exploitation with fair wages, modern oversight, and economic dignity.
Sign this petition, leave a comment detailing your personal experience, and demand structural fairness for all those working tirelessly for others. To build real, inescapable political and institutional leverage in California, you need 1,000 verified signatures as your minimum baseline. Will you sign? https://www.change.org/fairpayforlmfts
"Never doubt that a small group of thoughtful, committed citizens can change the world; indeed, it's the only thing that ever has." — Margaret Mead
#EqualPay #FairPay #GenderGap #EndSexismInLMFT #FairPayForLMFTs #FairPayForMFTtrainees #FairPayForAMFTs #FairPayforTherapists

110
The Issue
Systemic sexism is deeply embedded in the severely outdated structure of education and licensing for Licensed Marriage and Family Therapists (LMFTs).
With 80% of the LMFT workforce being female in 2026, women continue to be systematically exploited through unfair, uncompensated practices masked as "training." It is wage theft.
While these systems claim to provide clinical experience, they unfairly enrich universities, licensing boards, commercial payers, and employers at the expense of therapists struggling to make ends meet under rigid, oppressive requirements.
These laws and regulatory structures are over 60 years old, anchored in mid-20th-century labor frameworks designed by male-dominated legislative bodies that viewed carework through an outdated, patriarchal lens. In 1963, the California State Senate had zero women. A legislature that was over 97% male drafted and voted on the foundational laws governing clinical training hours, supervision, and practice restrictions. This system strips women of economic freedom, trapping pre-licensed clinicians in engineered dependency. It is not just a professional hurdle it is a structural barrier to self-determination and financial independence.
California’s 3,000-hour mandate was modeled in the 1960s on an unrealistic 40-hour direct-care workweek. In modern practice, a sustainable 20-session client load generates 20 uncompensated hours of administrative and supervisory labor. What lawmakers framed as a two-year milestone is functionally a three- to five-year economic bottleneck one that traps and extracts years of unpaid labor from a predominantly female workforce and turns a master’s-level health license into an engine of gendered financial hardship.
The Bureaucratic Gauntlet: Engineered Exhaustion & Wage Theft
To earn a license in mental health, practitioners are subjected to an over-engineered, Kafkaesque administrative gauntlet that goes far beyond professional preparation it is designed to exhaust, gatekeep, and extract unpaid labor. The sad truth is that roughly 40% to 50% of people who graduate with an MFT degree ultimately achieve full licensure.
- The 3,000-Hour Trap: Pre-licensed clinicians are forced to navigate rigid, arbitrary sub-quotas mathematically balancing hundreds of mandatory hours across micro-categories like couples therapy, family systems, and specialized clinical settings all while wrestling with relentless weekly tracking targets and perfect 5:1 and 10:1 ratios for supervision.
- Pay-to-Play Compliance: Therapists must absorb thousands of dollars in out-of-pocket costs for mandatory continuing education (CE) units, specialized clinical certifications, supervision fees, and complex tracking software just to maintain their livelihood. In male-dominated technical fields, employers routinely absorb compliance and training overhead as a standard cost of business. In mental health, the financial and administrative burden is pushed entirely onto underpaid workers.
- The 36-hour Continuing Education (CE) requirement is an ongoing financial and administrative tax imposed every renewal cycle on mental health professionals. Therapists are forced to pay out-of-pocket for coursework and lose valuable clinical income just to maintain their licenses, whereas male-dominated technical fields routinely absorb these exact professional development costs as employer-provided overhead.
Real-World Proof of Pipeline Exploitation
- Sub-Minimum Wages for Master’s-Level Professionals: Associates earn just 40%–45% of the market rate. Cedars-Sinai—one of California's top health systems—pays pre-licensed clinicians a mere $21/hour on a mandatory 3-year contract with zero health benefits. Male dominated masters level careers offer 100% market rate.
- Hostile Barriers for Caregivers: Compulsory evening hours at health-tech agencies (e.g., Daybreak) conflict directly with peak caregiving times when parents need to be with their children. Restrictive site policies—like Airport Marina Counseling Center’s 3-hour interview process offered only a few times per year further exclude working parents.
- The Privilege Floor: Only a hardworking 10% of women in California hold a Master’s degree. Forcing clinicians through 3,000 post-graduate hours of unpaid or underpaid labor assumes they have external financial support, pricing out working-class women and single parents
The Four Drivers of Systemic Gender Exploitation
1. The Devaluation of "Carework" & The "Pink-Collar" Wage Penalty
Historically, patriarchal economics categorized emotional labor, active listening, and relationship maintenance not as specialized clinical skills, but as "natural" feminine traits. Because nurturing is treated as an intrinsic duty rather than an earned competency, female-dominated professions suffer a severe wage penalty: as an industry becomes majority-female, its compensation and prestige drop relative to male-dominated fields requiring equivalent degrees.
2. Paternalistic Gatekeeping & The Caregiver Ceiling
The massive 3,000-hour requirement is a 40 year old relic with exploitative 40% fee splits operates on the outdated assumption that female clinicians are secondary earners relying on a spouse’s income, have no healthcare needs or labor floor. There is no consideration on the idea that women want autonomy and economic freedom. Combined with a lack of subsidized childcare and flexible career pacing, women are expected to caretake at home, work, and for aging parents without support any institutional support. It does not consider the workforce of today.
3. The "Glass Escalator," The "Glass Ceiling," & The "Gilded Tier"
Structural authority remains concentrated at the top, regardless of workforce demographics. In male-dominated fields, women face the classic Glass Ceiling: while entering at equal rates, by age 40 only 30% make it into executive leadership.
In female-dominated fields like LMFT where 80% of therapists are women the system operates on the Glass Escalator: men who enter the field rise disproportionately faster to executive director positions, board chairs, and high-level administrative roles. Meanwhile, the apex of the commercial mental health industry for example keynote speakers, certification training gurus, and health-tech broker overlords remain heavily male-dominated, leaving the overwhelmingly female workforce governed by institutions that profit off their extracted labor. Also, these additional commercial modality trainings have no real over-sight, but many rules for therapists and can take an additional 2-3 years and $10,000-$20,000 in additional investment to compete in the field.
4. The Institutional Pyramid Scheme
- Venture-Backed Health Tech (Lyra, Grow, Headway, Alma): Capture $5B+ valuations by monetizing the gap between high corporate billing rates and capped therapist payouts while shifting non-clinical admin labor onto unpaid clinicians.
- State Licensing Boards (e.g., California BBS): Mandate 3,000 hours without establishing wage floors, overtime protections, or fee-split limits, trapping associates in a captive workforce. The 3,000-hour mandate holds master's-level therapists to a doctoral-scale post-graduate standard and bottleneck without providing any of the structural protections, W-2 benefits, or federal funding guaranteed in doctoral medical residencies. While prescribing providers like Nurse Practitioners enter independent practice immediately upon graduation, therapy associates are forced through a multi-year apprenticeship that disproportionately exploits relational carework for profit under the guise of an arbitrary, legacy training metric.
- Universities & Graduate Programs: Charge full tuition while relying on uncompensated student labor to build community partnerships instead of funding internal paid clinics. Also, requiring students to pay out of pocket for 16 sessions of their own therapy with a licensed therapist.
- Commercial Insurers (Kaiser, Anthem, Blue Shield): Refuse to panel associates directly, capturing employer premiums while fostering burnout environments.
7 Demands for Policy Reform
- Mandate Pre-Licensed Insurance Billing: Commercial insurers, Medi-Cal, and Medicare must reimburse pre-licensed clinicians under a supervisor’s NPI to unlock immediate living wages.
- State-Funded Mental Health Residencies: Public health budgets and general fund grants must directly subsidize Associate salaries and agency overhead as an essential public health investment.
- Pay for ALL Hours Worked: End piece-rate exploitation. Require employers to pay for every required work hour—including note-writing, client assessments, crisis management, and mandatory supervision.
- Establish Industry Fee-Split Standards: Cap private practice revenue extraction by establishing clear industry standards (e.g., 60/40 or 65/35 in favor of the Associate).
- Enforce Strict Mental Health Parity: Force insurance commissioners to equalize behavioral health reimbursement rates with medical/surgical specialties to raise financial standards across the field.
- Eliminate Board Bottlenecks: Fully fund licensing boards to eliminate months-long administrative delays that lock clinicians out of the active workforce while carrying massive debt. Board of Behavioral Sciences (BBS) to initiate an occupational and comparative analysis of the 3,000-hour mandate.
- Hold Universities & Sites Accountable: Re-evaluate barriers to entry, audit practicum sites for labor mistreatment, oppressive and unreasonable requirements, and dismantle systems built on uncompensated carework.
Gender-Equity Crisis and Systemic Labor Exploitation, new AMFT Registrations: Roughly 3,500 to 4,000 new Associate Marriage and Family Therapists (AMFTs) register with the BBS each year after graduating from their master's programs and receiving their degrees. Active Total Pool: At any given time, the state maintains a total active pool of roughly 15,000 to 18,000 active AMFTs working across California to complete their required hours. Forcing thousands of uncompensated hours on a predominantly female workforce during a mental health crisis is an equity failure that must be dismantled.
Stand With Us: End the Exploitation, Provide Fair Pay and Demand Structural LMFT Licensing Reform, advanced degrees require advanced compensation. California’s mental health providers deliver life-saving care it's time to replace institutional exploitation with fair wages, modern oversight, and economic dignity.
Sign this petition, leave a comment detailing your personal experience, and demand structural fairness for all those working tirelessly for others. To build real, inescapable political and institutional leverage in California, you need 1,000 verified signatures as your minimum baseline. Will you sign? https://www.change.org/fairpayforlmfts
"Never doubt that a small group of thoughtful, committed citizens can change the world; indeed, it's the only thing that ever has." — Margaret Mead
#EqualPay #FairPay #GenderGap #EndSexismInLMFT #FairPayForLMFTs #FairPayForMFTtrainees #FairPayForAMFTs #FairPayforTherapists
The Decision Makers


Petition Updates
Share this petition
Petition created on September 9, 2026