

End Labor Exploitation in Therapy: Demand Paid MFT Training & Fair Associate Pay
The Issue
Sexism is deeply embedded in the whole system and structure of education and in the licensing processes for Licensed Marriage and Family Therapists (LMFTs). As someone who has been personally affected by these inequities, I am calling for a long overdue change and policy reform. With 80% of the LMFT workforce being female, it is unacceptable that women continue to be disproportionately exploited through unfair practices masked as "training". It is wage theft.
The prevalence of compulsory year long unpaid labor in the form of internships/practicums or so-called "training" only exacerbates the problem. While these systems are claimed to provide experience, they unfairly benefit employers at the expense of therapists who struggle to make ends meet and fit into some very rigid practicum requirements while performing essential services. It's time to dismantle these barriers and create a more equitable environment for all future LMFTs.
Many MFT associates are earning only 40%-45% of the market rate for their work. This egregious underpayment undervalues their contributions and perpetuates a culture of inequality within the mental health profession. The dedication, high level education and expertise in this field deserve recognition and fair compensation, not exploitation. In many cases, without standard benefits like medical, dental or retirement savings while working in the healthcare industry.
To address these injustices, I urge policymakers, insurance corporations, universities, health tech, and licensing bodies to reformulate the policies surrounding LMFT training and wages. Setting clear wage standards for trainees and associate roles would be a significant step forward. Implementing incentives for fair pay could also balance disparities and uphold the integrity and value of mental health professions.
Let's stand together to support hardworking therapists and demand that their labor be appropriately valued. Join me in petitioning for systemic change that promotes equal pay and recognizes the vital role these professionals play in supporting families and communities. Sign this petition to demand fairness and equality for all those working tirelessly for others. #EqualPay #FairPay #GenderGap #EndSexismInLMFT
Here is what needs to be fixed to end the systematic exploitation of pre-licensed clinicians:
- Policy Makers, BBS and Universities need to re-evaluate barriers to entry and the whole system that has embedded unpaid and underpaid labor into graduate programs and licensure. A system designed to penalize care workers most of which are female.
- Insurers Must Panel Associates: Commercial insurance, Medi-Cal, and Medicare must reimburse pre-licensed clinicians under a supervisor’s NPI. Unlocking insurance billing eliminates the reliance on cash-pay clients and creates the immediate revenue needed to pay Associates a living wage.
- State-Funded Mental Health Residencies: Public health budgets and general fund grants must directly subsidize Associate salaries and agency overhead, treating pre-licensed clinical training as an essential public health investment rather than cheap agency labor.
- Compensation for All Hours Worked: End piece-rate exploitation. Labor laws must require employers to pay clinicians for every required work hour—including note-writing, client assessments, crisis management, and mandatory supervision.
- Increased Group Practice Fee-Splits: Establish clear industry standards around private practice revenue splits (e.g., 60/40 or 65/35 in favor of the Associate), stopping practice owners from taking 60–70% of an Associate's billable rate.
- Enforce Strict Mental Health Parity: Force insurance commissioners to hold payers accountable, equalizing behavioral health reimbursement rates with medical and surgical specialties to raise the financial floor for the entire field.
- Fix Board Bottlenecks: Fully fund licensing boards to eliminate months-long administrative delays that freeze clinicians out of the active workforce while holding massive student debt.
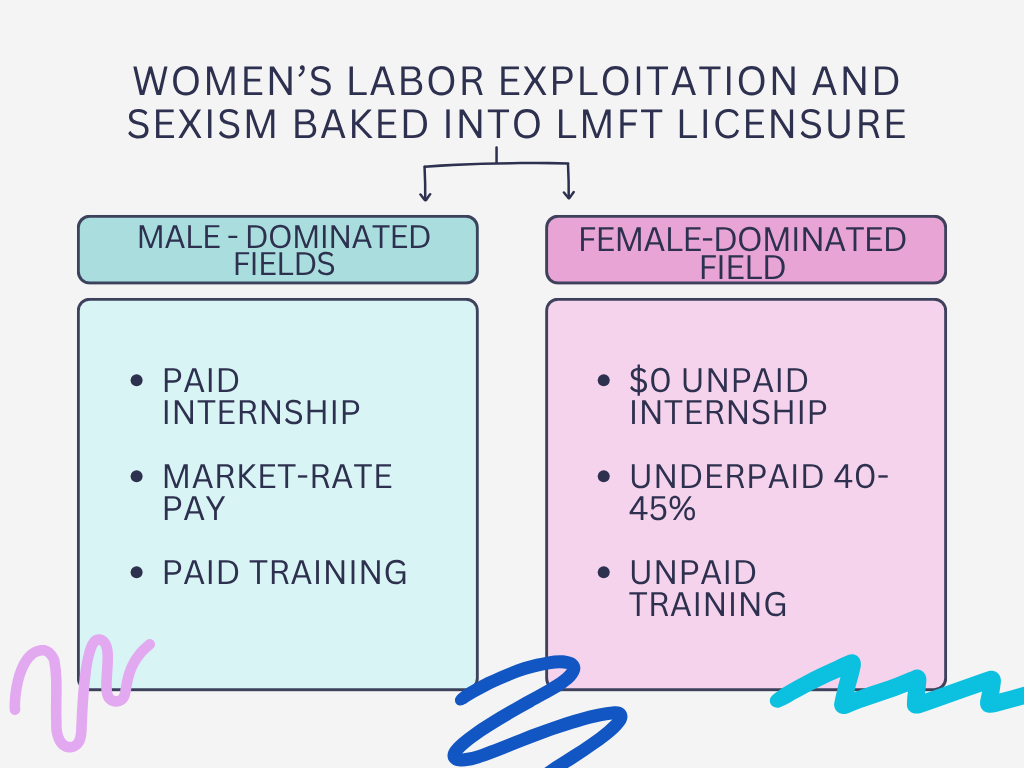
The structural exploitation built into the LMFT licensure pipeline is directly rooted in centuries of societal sexism and the economic devaluation of feminized labor.
The Devaluation of "Carework" as Innate Labor Historically, patriarchal economic systems categorized emotional labor, active listening, and relationship maintenance not as specialized professional skills, but as "natural" feminine traits. Because society viewed nurturing as an intrinsic duty rather than a earned competency, work associated with caregiving—nursing, teaching, social work, and therapy—was systematically underfunded. This cultural assumption creates the baseline expectation that female clinicians should accept working for "altruism" or "passion" rather than fair, livable compensation. Also, women continue to carry a disproportionate share of domestic and caregiving responsibilities. Without institutional support, such as subsidized childcare, paid family leave, and flexible career pacing, this imbalance acts as a structural ceiling. It's unrealistic to expect a woman to caretake for children and family at home, caretake at work and caretake aging parents too.
The "Pink-Collar" Wage Penalty Sociological research shows a direct phenomenon: as an industry becomes overwhelmingly female-dominated, the overall compensation and prestige of that industry decline relative to male-dominated sectors requiring equivalent degrees. MFTs complete rigorous Master's programs, sit for standardized board exams, and hold advanced clinical knowledge, yet the regulatory framework treats their graduate practicums as unpaid volunteerism.
Paternalistic Gatekeeping and Economic Control The requirement of 3,000 post-graduate supervised hours in varied categories and numbers, paired with exploitative 40% (or lower) fee splits, functions as economic gatekeeping. Historically, systems designed by male leadership assumed female workers were secondary earners relying on a male spouse's primary income. Forcing associates into years of poverty-level wages or forced unpaid labor assumes clinicians have external financial support—effectively pricing out working-class women, single parents, and marginalized clinicians while enriching established practice owners. Also, called monopsonistic labor exploitation
The "Glass Escalator" Effect In female-dominated professions, structural authority frequently remains concentrated at the top. Men who enter pink-collar fields statistically rise faster to executive director positions, board chairs, and high-level administrative roles—the "glass escalator". This creates a system where a workforce that is 80–90% female is governed by predominately male regulatory committees, corporate health plan CEOs, and legislators who maintain institutional policies that extract profit from mainly female pre-licensed labor.
The Gilded Tier, while over 80% of frontline therapists, trainees, and associates are women. However, the apex of the commercial mental health industry ("gurus", trainings, certificates, keynote speakers, courses, events, and health tech broker overlords) is heavily dominated by men.
The mental health field is structured like a classic corporate pyramid scheme built on gendered exploitation

23
The Issue
Sexism is deeply embedded in the whole system and structure of education and in the licensing processes for Licensed Marriage and Family Therapists (LMFTs). As someone who has been personally affected by these inequities, I am calling for a long overdue change and policy reform. With 80% of the LMFT workforce being female, it is unacceptable that women continue to be disproportionately exploited through unfair practices masked as "training". It is wage theft.
The prevalence of compulsory year long unpaid labor in the form of internships/practicums or so-called "training" only exacerbates the problem. While these systems are claimed to provide experience, they unfairly benefit employers at the expense of therapists who struggle to make ends meet and fit into some very rigid practicum requirements while performing essential services. It's time to dismantle these barriers and create a more equitable environment for all future LMFTs.
Many MFT associates are earning only 40%-45% of the market rate for their work. This egregious underpayment undervalues their contributions and perpetuates a culture of inequality within the mental health profession. The dedication, high level education and expertise in this field deserve recognition and fair compensation, not exploitation. In many cases, without standard benefits like medical, dental or retirement savings while working in the healthcare industry.
To address these injustices, I urge policymakers, insurance corporations, universities, health tech, and licensing bodies to reformulate the policies surrounding LMFT training and wages. Setting clear wage standards for trainees and associate roles would be a significant step forward. Implementing incentives for fair pay could also balance disparities and uphold the integrity and value of mental health professions.
Let's stand together to support hardworking therapists and demand that their labor be appropriately valued. Join me in petitioning for systemic change that promotes equal pay and recognizes the vital role these professionals play in supporting families and communities. Sign this petition to demand fairness and equality for all those working tirelessly for others. #EqualPay #FairPay #GenderGap #EndSexismInLMFT
Here is what needs to be fixed to end the systematic exploitation of pre-licensed clinicians:
- Policy Makers, BBS and Universities need to re-evaluate barriers to entry and the whole system that has embedded unpaid and underpaid labor into graduate programs and licensure. A system designed to penalize care workers most of which are female.
- Insurers Must Panel Associates: Commercial insurance, Medi-Cal, and Medicare must reimburse pre-licensed clinicians under a supervisor’s NPI. Unlocking insurance billing eliminates the reliance on cash-pay clients and creates the immediate revenue needed to pay Associates a living wage.
- State-Funded Mental Health Residencies: Public health budgets and general fund grants must directly subsidize Associate salaries and agency overhead, treating pre-licensed clinical training as an essential public health investment rather than cheap agency labor.
- Compensation for All Hours Worked: End piece-rate exploitation. Labor laws must require employers to pay clinicians for every required work hour—including note-writing, client assessments, crisis management, and mandatory supervision.
- Increased Group Practice Fee-Splits: Establish clear industry standards around private practice revenue splits (e.g., 60/40 or 65/35 in favor of the Associate), stopping practice owners from taking 60–70% of an Associate's billable rate.
- Enforce Strict Mental Health Parity: Force insurance commissioners to hold payers accountable, equalizing behavioral health reimbursement rates with medical and surgical specialties to raise the financial floor for the entire field.
- Fix Board Bottlenecks: Fully fund licensing boards to eliminate months-long administrative delays that freeze clinicians out of the active workforce while holding massive student debt.
The structural exploitation built into the LMFT licensure pipeline is directly rooted in centuries of societal sexism and the economic devaluation of feminized labor.
The Devaluation of "Carework" as Innate Labor Historically, patriarchal economic systems categorized emotional labor, active listening, and relationship maintenance not as specialized professional skills, but as "natural" feminine traits. Because society viewed nurturing as an intrinsic duty rather than a earned competency, work associated with caregiving—nursing, teaching, social work, and therapy—was systematically underfunded. This cultural assumption creates the baseline expectation that female clinicians should accept working for "altruism" or "passion" rather than fair, livable compensation. Also, women continue to carry a disproportionate share of domestic and caregiving responsibilities. Without institutional support, such as subsidized childcare, paid family leave, and flexible career pacing, this imbalance acts as a structural ceiling. It's unrealistic to expect a woman to caretake for children and family at home, caretake at work and caretake aging parents too.
The "Pink-Collar" Wage Penalty Sociological research shows a direct phenomenon: as an industry becomes overwhelmingly female-dominated, the overall compensation and prestige of that industry decline relative to male-dominated sectors requiring equivalent degrees. MFTs complete rigorous Master's programs, sit for standardized board exams, and hold advanced clinical knowledge, yet the regulatory framework treats their graduate practicums as unpaid volunteerism.
Paternalistic Gatekeeping and Economic Control The requirement of 3,000 post-graduate supervised hours in varied categories and numbers, paired with exploitative 40% (or lower) fee splits, functions as economic gatekeeping. Historically, systems designed by male leadership assumed female workers were secondary earners relying on a male spouse's primary income. Forcing associates into years of poverty-level wages or forced unpaid labor assumes clinicians have external financial support—effectively pricing out working-class women, single parents, and marginalized clinicians while enriching established practice owners. Also, called monopsonistic labor exploitation
The "Glass Escalator" Effect In female-dominated professions, structural authority frequently remains concentrated at the top. Men who enter pink-collar fields statistically rise faster to executive director positions, board chairs, and high-level administrative roles—the "glass escalator". This creates a system where a workforce that is 80–90% female is governed by predominately male regulatory committees, corporate health plan CEOs, and legislators who maintain institutional policies that extract profit from mainly female pre-licensed labor.
The Gilded Tier, while over 80% of frontline therapists, trainees, and associates are women. However, the apex of the commercial mental health industry ("gurus", trainings, certificates, keynote speakers, courses, events, and health tech broker overlords) is heavily dominated by men.
The mental health field is structured like a classic corporate pyramid scheme built on gendered exploitation
The Decision Makers


Petition Updates
Share this petition
Petition created on September 9, 2026